


A. Introduction
A2. DKA의 정의
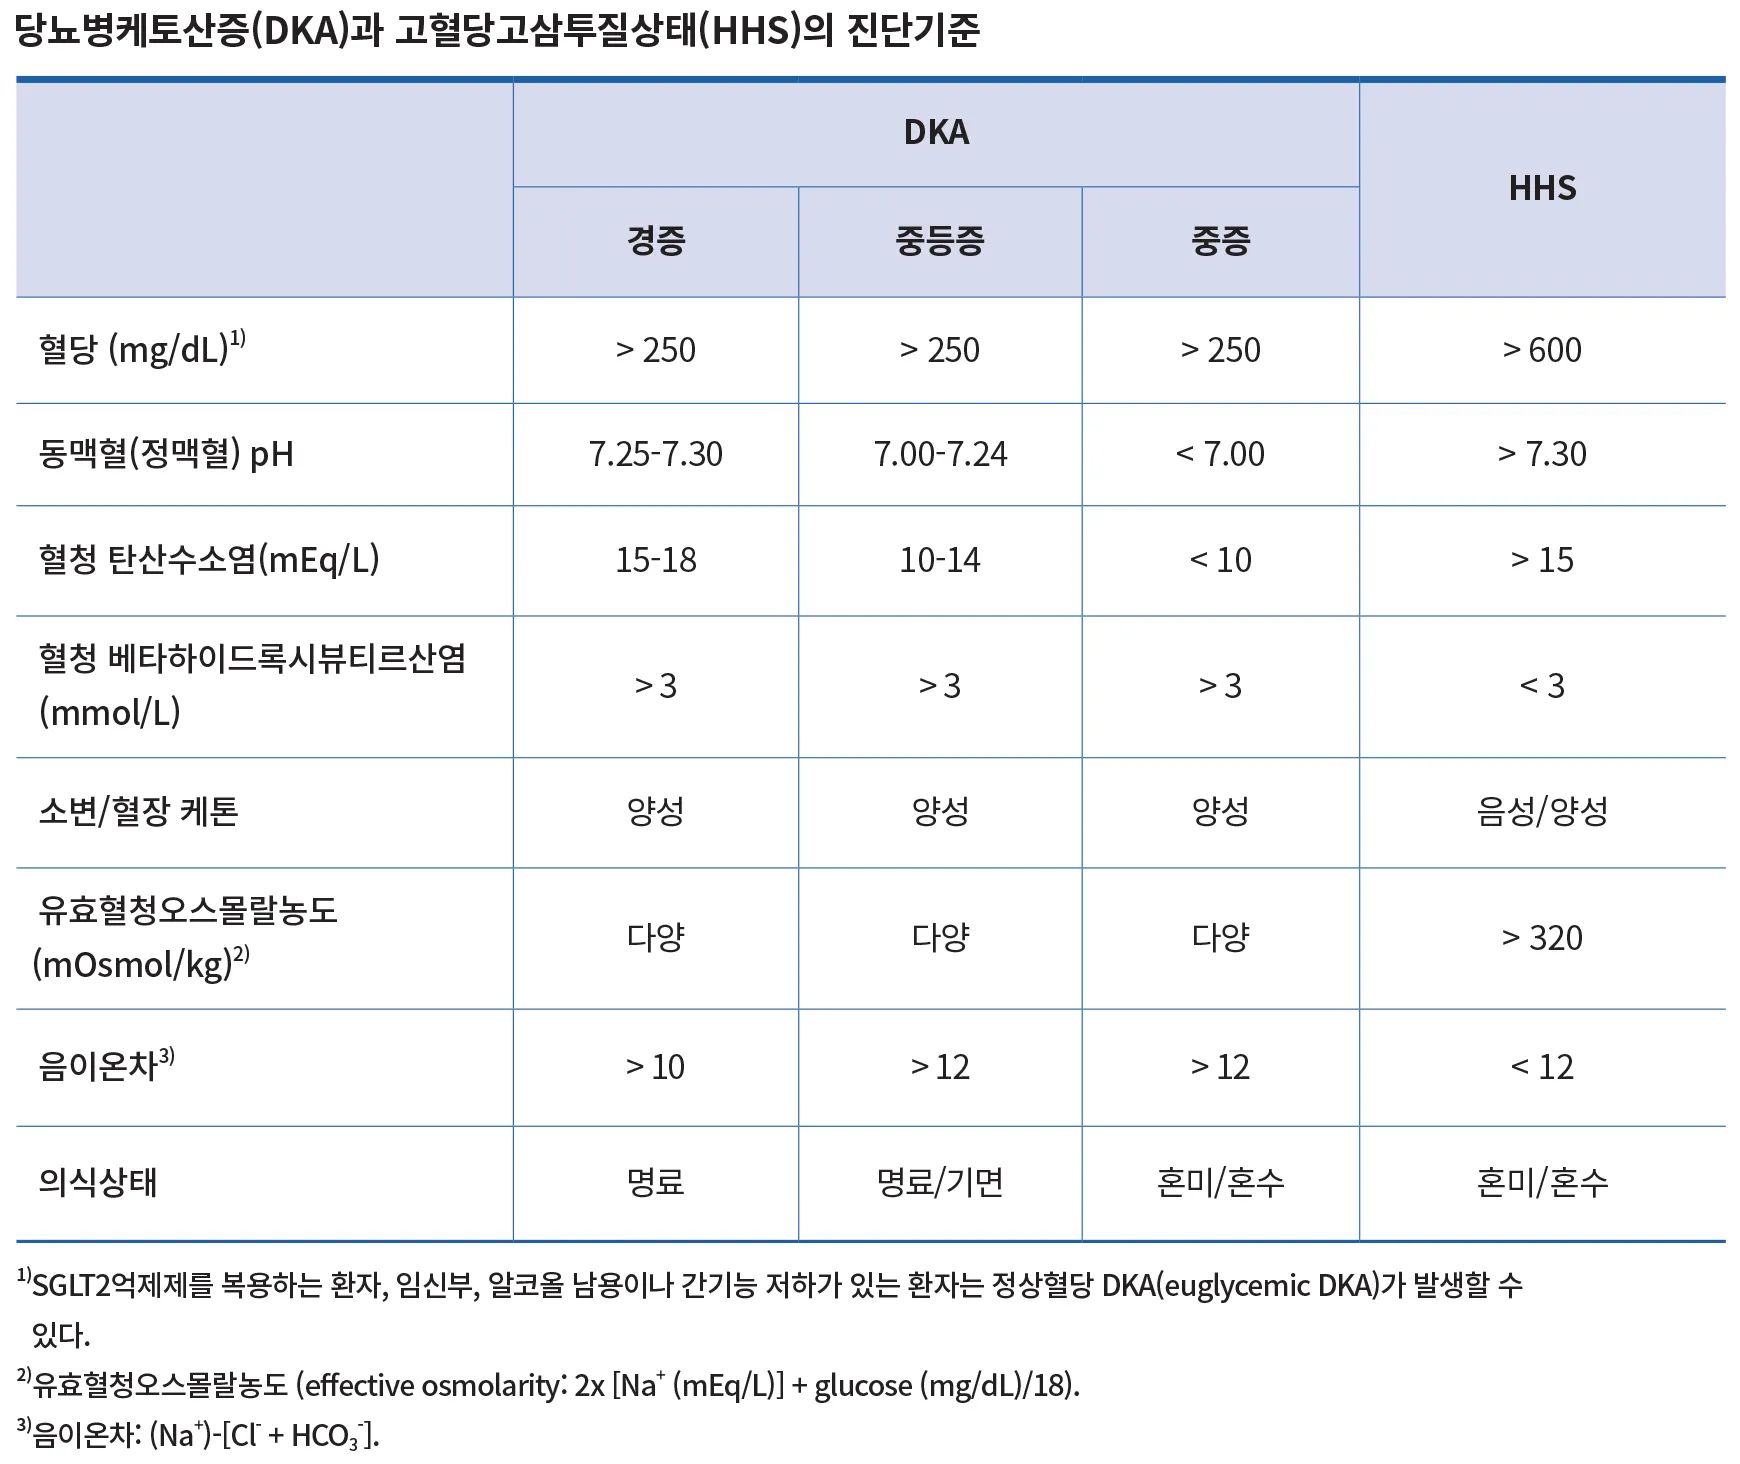
: DKA와 HHS는 Ketoacidosis와 hyperglycemia정도에 따라서 구분할 수 있다.
: 정의는 아래 표와 같다

•
DKA는 metabolic acidosis가 major finding이다.
•
serum glucose는 일반적으로 800mg/dL 미만이다 (대개 350~500mg/dL)
그러나 comatose한 환자는 900을 넘는 경우도 있다.
또는 250mg/dL미만으로 정상 수준을 보이는 경우도 있다 (euglycemic DKA)
•
HHS에서는 ketosis는 경미하거나 없고, serum glucose가 1000mg/dL를 넘는 경우가 많다.
•
TBW deficit

A4. DKA의 원인 (Introduction 참조)
당뇨병성 케톤산증의 주요 원인들:
• 일일 인슐린 주사 누락 또는 감량
• 인슐린 펌프 카테터의 이탈/폐색
• 감염
• 임신
• 갑상선기능항진증, 갈색세포종, 쿠싱증후군
• 약물 남용 (코카인)
• 약물: 스테로이드, 티아지드, 항정신병약, 교감신경유사제 | • 열관련 질환
• 뇌혈관 사고
• 위장관 출혈
• 심근경색
• 폐색전증
• 췌장염
• 중증 외상
• 수술 |
B. Clinical Features
B1. DKA 의 임상적 특성
① Hyperglycemia ② Volume depletion ③ Acidosis 와 관련.
B2. Symptom
(1) Nausea & Vomiting
(2) 복통
(3) 의식변화
(4) Tachycardia
(5) Orthostatic hypotension
(6) Poor skin turgor & dry mucous membranes
(7) Kussmaul respirations
(8) Increased rate and depth of breathing
(9) Fruity odor on the breath (acetone 특유의 냄새)
(10) 저체온
1.
Alteration of consciousness has been reported to correlate better with elevated
serum osmolarity (>320mOsm/L) than with severity of metabolic acidosis.
C. Diagnosis and Laboratory Evaluation
산-염기 장애에 대한 6단계 분석을 적용
1) albumin adjusted AG = AG + 2.5 (4.0 - albumin)
2) Delta gap = (albumin adjusted anion gap − 12) − (24 − HCO3−)
: MAk 동반 : Delta gap > 6
: NAGMA 동반 : Delta gap < -6
3) pH and pCO2 : Primary acid-base 이상을 판단
4) Winter’s formula
primary MA 시 expected pCO2 = 1.5 × HCO3 − + 8 ± 2
primary MAk 시 expected pCO2 = 40 + 0.7× (HCO3−- 24) ± 5
5) effective osmolality = 2 × Na+ + glucose/18
C1. DKA 진단기준 Dx
(1) DKA 세 가지 개별적 기준
•
전통적인 산혈증 DKA : pH ≤7.3 또는 중탄산염 ≤18mmol/L의 케톤증
•
AG 증가 DKA: pH 또는 중탄산염에 관계없이 AG > 16mmol/L 이상인 케톤증
•
β-OHB ≥3.0mmol/L. (DKA의 조기 발견에 유용함)
β-OHB는 DKA에서 우세한 케톤체를 차지하며 정량적으로 측정가능
3mmol/L의 point capillary β-OHB는 중탄산염 <20mmol/L 또는 음이온 갭 >16mmol/L과 상관관계가 있는 것으로 나타났으며, 따라서 β-OHB ≥3.0mmol/L은 중증 케톤산증을 감지하는 독립적인 파라미터로 사용될 수 있으며 민감도는 100%, 특이도는 94%.
(2) 기타 기준
•
Glucose >250 mg/dL
•
Anion gap (AG) >10
•
Bicarbonate <15 mEq/L
•
pH <7.3
•
Moderate ketonuria or ketonemia
(3) 2009년 미국 당뇨병 협회(ADA) DKA의 진단 기준
•
혈당 ≥250 mg/dL
DKA 환자는 혈당이 250mg/dL 미만인 저혈당성 DKA로 나타날 수 있습니다, 이는 종종 sodium-glucose cotransporter-2 inhibitors를 복용하거나 starvation이 동반되어 있을 때 발생
•
혈청 또는 소변 케톤의 존재
•
pH ≤7.3으로 정의되는 산증,
•
중탄산염 ≤18mmol/L 또는 음이온 갭 >10-12mmol/L.
C2. Ketone body
(1) Metabolic acidosis 와 ketonuria 의 원인
(2) AcAc + NADH ⇌ βHB + NAD 의 평형에서 βHB 쪽으로 기운다.
•
사실 βHB을 detection하는 검사가 reliable하나 βHB test는 available 하지 않다.
•
일반적으로 urine 과 serum 의 ketone detection을 위해 nitroprusside reagent가 널리 사용되나
AcAc detection 하므로 reliability가 떨어진다.
C3. AG
•
Acidosis가 masking되는 경우, elevated AG이 metabolic acidosis의 유일한 단서가 될 수 있다.
C4. VBGA
•
Venous와 arterial pH 사이에 correlation이 높아 ABGA 대신 VBGA를 사용할 수 있다.
•
Venous pH는 arterial 보다 약 0.03 정도 낮게 측정됨.
C5. Serum K
•
total body K보다 높게 측정되고, serum Na은 total body Na보다 낮게 측정될 수 있다.
D. Differential Diagnosis
D1. DKA 감별진단 (Tintinalli 9th, Table 225-3)
(1) Alcoholic ketoacidosis
(2) Starvation ketoacidosis
(3) Renal failure
(4) Lactic acidosis,
(5) Ingestion (salicylates, ethylene glycol, methanol)
•
Metformin을 복용 중인 new-onset renal insufficiency 환자는 type B (aerobic) lactic
acidosis가 발생할 위험성이 있다.
D2. Tintinalli 9th, Table 227-3

E. Treatment

•
Treatment goal
(1) Glucose <200mg/dL
(2) [HCO3-] ≥18
(3) Venous pH >7.3
•
치료 우선순위
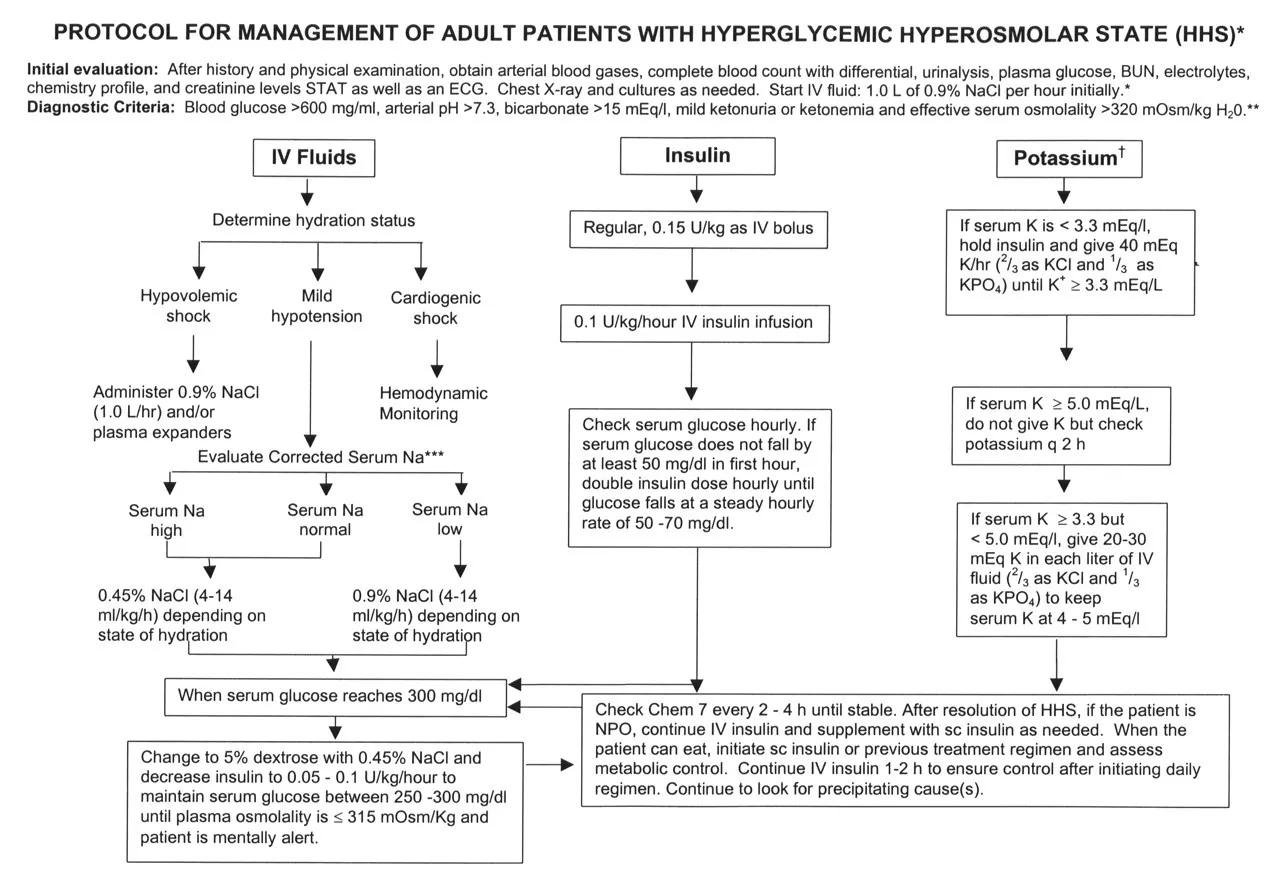
Volume first and foremost!! → Correction of K deficit → Insulin
•
Goal 달성할 때까지 Lab. (glucose, K+, AG), v/s, 의식 수준, I/O 2시간마다 f/u
E1. Fluid replacement
•
평균적으로 5~10L(100cc/kg)의 water deficit (Rosen 8th: 3-5L deficit)
•
7~10 mEq/kg의 Na+ deficit
•
N/S으로 시작 (최적의 속도는 환자 임상 상태에 따라 다름)
•
NS은 intracellular fluid loss를 교정을 위한 free water를 제공하지는 못하나, extracellular
osmolarity가 급격하게 떨어지는 것을 막아준다.
(1) Stable
--> corrected Na 에 따라 N/S or Half Saline으로 Hydration (200cc/hr ~ 1000cc/hr)
•
NS 첫 1L를 첫 30분 이내 투여
◦
Fluid 2L over 0~2hrs → 다음 2L over 2~6hrs → >2L over 6~12hrs
(Total water deficit의 50%를 처음 12시간 동안 투여)
◦
BST 250mg/dL에 도달하면 5% dextrose in 0.45% saline으로 변경.
◦
탈수가 심하지 않은 경우 N/S 500mL/h for 4hrs
◦
일단 먹기 시작하면, glucose infusion은 stop 할 수 있음.
(2) Hypovolemic shock (HF가 없는)
•
15~20 mL/kg LBW / hr 속도로 투여 (보통 성인의 경우 1L/hr) - 첫 2시간 동안
•
Balanced crystalloid solution 사용가능 (최근에는 이게 더 낫다는 연구도 있다)
•
Hyponatremia 이면 → 0.9% saline 250-500mL/h
•
Eunatrema/hypernatremia 이면 → 0.45% saline 250-500mL/h
•
첫 4시간 내는 최고 50 mL/kg/hr 이하
•
2~3 시간 째 에는 hydration 상태, 전해질, 소변량을 고려하여 속도 조절
•
Blood glucose < 250mg/dL 이면 → 5% dextrose 로 변경하여 투여
•
0-2hr 2L / 2-6hr 2L / 6-12hr 2L → 50% of total water deficit
E2. Insulin
•
세포 내로 Glucose이동 및 Ketoacidosis 해결 위해 DW를 주더라도 가능한 Insulin 은 계속투여
(1) Low dose regular insulin의 continuous infusion이 가장 안전
•
일정한 blood concentration 유지 가능
•
Dose adjustment의 flexibility가 높음.
(2) 일단 hypokalemia (K+<3.3)가 배제되면,
•
Insulin 0.1 u/kg bolus (optional in adults, not recommended in children)
→ 0.1 u/kg/hr cont. infusion (이렇게 쓰면 BST 50~75mg/dL/h씩 감소)
•
Initial bolus : RI 0.15U/kg bolus (60Kg인 경우 Humulin R 9U IVS) : EM교과서에는 옵션임
•
유지 : RI 0.1 U/kg/hr (60 kg인 경우 Humulin R 100U + N/S 100 mL 6cc/hr)
•
Response (첫 1시간 동안 BST 10%의 감소)가 없으면,
IV bolus (0.14 unit/kg)를 사용하거나, 다른 대안은 insulin infusion rate을 1unit/h씩 증량
(3) SC insulin
•
Uncomplicated mild to moderate DKA에서 rapid SC insulin 은 대안이 될 수 있다.
•
SC rapid-acting insulin 0.2u/kg → 0.1u/kg q1hr
혹은 SC rapid-acting insulin 0.3u/kg → 0.2u/kg q2hr
•
BST <250 될 때까지 사용하며 그 뒤에는 용량을 반으로 줄여서 DKA가 resolution될 때까지 사용
(4) Insulin IV infusion은 다음 사항을 다 만족할 때까지 사용한다.
•
Glucose<200mg/dL
•
Serum bicarbonate level > 15 mEq/L
•
Venous pH > 7.3 and/or calculated anion gap 정상화 될 때까지
•
Insulin infusion을 stop 했을 때 Hyperglycemia나 DKA가 재발하는 것을 막기 위하여 기저 SC insulin으로 전환한다.
◦
기저 인슐린 투여 관련 미국당뇨병학회(ADA) 가이드라인
▪
2009년 이후 업데이트 되지 않음
▪
DKA가 해결된 후 기저 인슐린을 투여할 것을 권장
DKA해소기준
- 혈당 수치 200mg/dL 미만
- 혈청 HCO3 ≥15mEq/L,
- 정맥 pH > 7.3 또는 계산된 AG ≤12 중 두 가지 기준 중 하나로 정의
◦
기저 인슐린 투여 관련 영국당뇨병학회 공동 가이드라인
▪
2023.3 개정
▪
정맥 인슐린 중단 후 12시간 내 혈당 ≥180 mg/dL로 정의되는 반동성 고혈당 발생을 줄이기 위해 위의 기준에 관계없이 DKA 진단 즉시 환자의 기저 인슐린을 재시작하거나 기저 인슐린을 0.25단위/kg로 새로 시작할 것을 제안 . 그림 1은 시기와 관련하여 이 두 지침 간의 관리 차이점을 강조

Guideline Recommendations on Introduction of Basal Insulin in the Management of Diabetic Ketoacidosis
E3. Potassium
(1) 대개 3~5mEq/kg의 K+ deficit 이 동반되나, initial lab에서는 높게 나온다.
(2) Initial serum K level이 실제 total body K 보다 높게 나오는 이유
•
The intracellular exchange of potassium for hydrogen ions during acidosis
•
The total-body fluid deficit
•
Diminished renal function
•
“pH 가 0.1 떨어질 때마다 serum K+ level 이 0.5mEq/L 증가한다“
(3) K replacement

•
3.3< initial K+ <5.3mEq/L : Urine output이 적절하면 적어도 4시간 이상 KCl 10mEq/h 보충
•
Initial K+ <3.3 mEq/L이면 10~15mEq/h로 보충. insulin therapy는 K+ >3.3 이 되면 시작.
•
Oral K replacement 는 안전하고 효과적이므로, 환자가 oral fluids 에 tolerable 해지면 바로 사용
•
첫 24시간 동안 보통 KCl 100~200mEq가 요구된다.

E4. Phosphate
(1) DKA시에 혈중 phosphate level은 종종 정상 혹은 증가된 것으로 보여진다.
→ Urinary loss가 증가된 것에 이차적으로 total-body phosphate deficit 이 반영되지 않았기 때문.
(2) Insulin therapy 동안 phosphate는 세포 내로 이동한다.
•
Hypophosphagemia 는 보통 insulin 치료 시작 24~48시간 후에 가장 심해지나,
ED에서 DKA에서 치료 목적의 K2PO4 IV 투여 기준은 확립되어 있지 않다.
(3) P < 1.0mg/dL 일 경우에만 IV K2PO4 2.5~5mg/kg 사용
•
P supplemental 중에 Ca level monitoring 시행해야 함
(4) IV phosphate 의 side effects
① Hyperphosphatemia ② Hypocalcemia,
③ Hypomagnesemia ④ Hypernatremia
⑤ Metastatic soft tissue calcifications ⑥ Volume loss from osmotic diuresis
(precipitation of calcium phosphate)
E5. Magnesium
(1) Osmotic diuresis 는 hypomagnesemia 의 원인이 될 수 있다.
(2) Hypomagnesemia 는 parathyroid H. secretion을 제한시켜 hypocalcemia 와 hyperphosphatemia를 유발할 수 있다.
(3) Mg < 2.0 mg/dL 이거나 증상이 있을 경우, magnesium sulfate 2g IV over 1hr
E6. Bicarbonate
•
Routine으로 사용하는 것은 권장되지 않는다.
•
Initial pH < 6.9에서 사용 그러나 pH >7.0 에는 사용하지 않는다.
•
성인에서 pH <6.9, 일 때 100mEq of sodium bicarbonate in 400mL of water
with 20mEq KCl at 200mL/hr를 2시간 동안, pH가 7.0 이상이 될 때까지 줄 수 있다.
•
pH 6.9~7.0 : bicarbonate 50 mmol (bicarbonate 2.5A + N/S 200 cc IV for 1hr)
•
pH < 6.9 : bicarbonate 100 mmol (bicarbonate 5A + N/S 400 cc IV for 2 hr)
DKA 에서 bicarbonate 투여시 고혈당/케톤산증 회복속도에 이득이 없고 저칼륨혈증/뇌부종의 위험이 더 높았다.
가이드라인에서는 7.0 도달까지 100mmol (2ample) 을 400mL에 혼합하여 2시간 동안 주입 고려
(1) Theoretical advantages
① Improved myocardial contractility ② Elevated ventricular fibillration threshold
③ Improved catecholamine tissue response ④ Decreased work of breath
(2) Disadvantage
① Hypokalemia 의 악화 ② Paradoxical CNS acidosis
③ Intracellular acidosis의 악화 ④ Oxyhemoglobin 해리곡선 좌측이동
⑤ Ketosis 호전 지연 ⑥ Lactate level 증가
⑦ Cerebral edema 악화 가능 ⑧ Hypertonicity and Na overload
F. Outcomes, complications, and mortality
F1. Complications related to acute disease
(1) Infection & MI : the main contributors to high mortality
F2. Lab F/U
•
ABGA, E', S.som. glucose, ketone bodies, U.osm/Na/K/Cl

F3. Complications related to therapy
(1) Cerebral edema
•
대개 치료 시작 전, 시작하고 4-12시간 사이, 48시간 이상 후에 발생.
•
Risk factor : Young age / New-onset DM / Excessive fluid (>4L/m2 of BSA)
•
Water & sodium deficit 의 gradual replacement & hyperglycemia의 slow correction으로
risk를 낮출 수 있다.
•
치료 : 신경학적 증상 (HA, Sz), 서맥 등 발생 시 IV mannitol (1~2g/kg)
혹은 3% hypertonic saline 5~10cc/kg over 30min
F3. Late complications
(1) Mortality는 주로 sepsis 혹은 pulmonary & cardiovascular complications (고령의 경우)이나
fatal cerebral edema(소아 & 젊은 성인의 경우) 때문이다.

G. Special populations
1.
Insulin pump를 사용하던 환자에서 DKA가 의심되는 경우
(1) Pump를 끄고, 다른 일반 환자처럼 치료
(2) Non-pump user에서 insulin infusion 치료 후 SC insulin으로 전환했던 것과 같이 pump를
사용하던 환자는 pump therapy를 다시 시작한다.
2.
임신 중에 DKA가 잘 생기는 이유
(1) 임신 중에는 fasting glucose가 정상적으로 낮아져 있어 상대적으로 insulin deficiency 상태가 되며, 정상적으로 counter-regulatory hormone level 이 증가되어 있다.
(2) 임신 중에는 vomiting과 UTI의 incidence도 증가된다.
(3) 임신 중에 보이는 chr. resp. alkalosis는 bicarbonate level의 감소를 낳고 이는 buffering
capacity 의 감소로 이어져 DKA가 발생하기 쉽다.
(4) DKA 산모의 hyperglycemia, acidosis, electrolyte balance의 교정이 최우선이다
