


•
Pleural effusion : 장측 (visceral) 흉막과 벽측 (parietal) 흉막 사이 잠재공간에 fluid가 찬 것
•
지속적인 fluid는 parietal pleura로부터 pleural space 안으로 분비가 되는데 이것은 visceral pleural microcirculation을 통해 흡수가 된다.
이 과정을 막거나 fluid를 증가시키는 요소가 있으면 pleural space에 effusion이 발생하게 된다.
G1. Clinical features
(1) Clinically silent에서부터 dyspnea와 pain 등이 발생할 수 있으며 신체 검진에서 percussion
dullness와 decreased breath sound를 나타낼 수 있다.

G2. Diagnosis
•
보통 x-ray, USG, CT 등으로 진단할 수 있다.
•
명확한 pleural effusion은 CXR lateral decubitus 또는 USG 상 10mm 이상의 두께로 보인다.
•
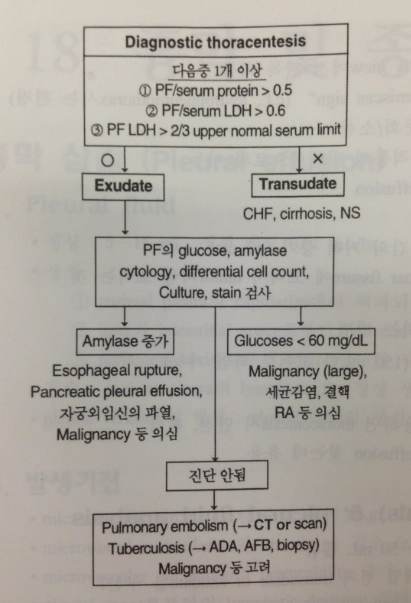
진단적 흉강 천자술을 통해 pleural fluid analysis를 할 수 있으며 원인을 파악할 수 있다.
G3. Diagnostic Tests
(1) Detection of exudative pleural effusion
•
Light criteria for pleural exudate – 아래 3개 중 하나
◦
Pleural fluid/serum protein ratio > 0.5 (가장 중요, 절대값 > 3.0 g/dL)
◦
Pleural fluid/serum LDH ratio > 0.6 (wjfeorkqt > 200 IU/L)
◦
Pleural fluid LD가 혈청 정상 상한치의 2/3 이상
⇒ 이 방법으로는 transudate 의 25%가 exudate로 분류됨.

•
Serum - Pleural fluid albumin gradient 측정
⇒ 차이가 1.2 g/dL 이상이면 위 기준에 관계없이 transudate

(2) Standard test for evaluation of pleural effusion
•
Serum protein & LDH
•
Pleural fluid protein & LDH
•
Pleural fluid Gram stain and culture to detect bacterial infection
•
Pleural fluid cell count
: Neutrophill prdedominance – parapneumonia, pulmonary embolism, pancreatitis
: Lymphocytic predominance – cancer, tuberculosis, postcardiac surgery
•
Glucose
: Low glucose seen in parapneumonic, malignant, tuberculosis and rheumatoid arthritis
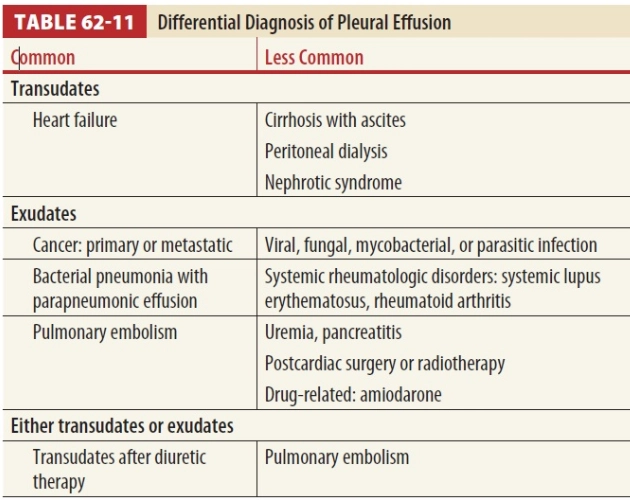
causes of pleural effusions
(3) Additional tests according to clinical circumstances
•
Cytology for malignancy
: Highest yield is with adenocarcinoma
: Much lower with squamous cell carcinoma
: Lymphoma or mesothelioma
•
Pleural fluid pH
: Normal pleural fluid pH around 7.64
: In parapneumonic effusion – pH < 7.10 predicts development of empyema or persistance
and indicates need for thoracostomy tube draiange
•
Pleural fluid amylase
: Elevated in pleural effusions due to pancreatitis or esophageal rupture
•
Mycobacterial and fungal stains and cultures : as suggested clinically
•
Tuberculosis pleural fulid markers
: PCR for mycobacterial DNA
: Pleural fluid adenosine deaminase (ADA) or pleural fluid interferon-γ



G4. Treatment
(1) Dyspnea at rest
•
흉강천자 1.0 ~ 1.5 L
•
너무 많은 양은 피한다. (re expansion pulmonary edema 발생 가능)
(2) Pleural empyema
•
Gross pus or organisms on Gram stain
•
Drainage with large-bore thoracostomy tubes
(3) parapneumonic effusions : controversial
•
need for thoracostomy tube drainage
- comorbid disease
- failure to respond to antibiotic therapy
- anaerobic organisms
- pleural fluid pH <7.10
- effusion involving >50% of the thorax
